


Steve Turner
Members
-
Joined
-
Last visited
Everything posted by Steve Turner
-
Community PostThis potentially looks very helpful. Preventable deaths tracker:
-
Content ArticleThe UK Government has opened a consultation on changes to the Mental Capacity Act (MCA) 2005 Code of Practice, and implementation of Liberty Protection Safeguards (LPS). This consultation is also seeking views on the LPS regulations, which will underpin the new system. This consultation applies to England and Wales and is open until 7 July 2022.
-
Community PostThis work has so much potential for improvements in patient safety. Will it link to Coroners prevention of future deaths reports? It's such a complex area, with so many threads and possibilities for learning. I used to work in a Mental Health Assertive Outreach Team and was greatly saddened by the high mortality rate from deaths through neglect or undetected (and treatable) physical illnesses.
-
Bb9eb4a8277e9d72dd837687465f4857Thank you for posting this. The actions resulting from Coroners' prevention of future deaths are vital for patient safety. I look through these reports when preparing clinical education sessions, and have included this link in my medicines and prescribing teaching resource page: https://www.judiciary.uk/subject/alcohol-drug-and-medication-related-deaths/
-
Bb9eb4a8277e9d72dd837687465f4857Thank you for posting this. Coroners' prevention of future deaths reports are important, and the actions resulting from them are vital for patient safety. I look through these reports when preparing clinical education sessions, and have included this link in my teaching resources: https://www.judiciary.uk/subject/prevention-of-future-deaths/ Unfortunately, I believe there is an inconsistency in when Coroners make these reports. For example, in the case of the death of Oliver McGowan, where no such report was made. This is a case study I use in my medicines and prescribing teaching work. I've also come across a press reports of a trust putting pressure on a Coroner not to make a prevention of future deaths report. I'm interested in people's views on this. Am I right in thinking that there is an inconsistency in how Coroners use their powers to make prevention of future deaths reports? Are there any other reported examples of trust's trying to put pressure on Coroners?
-
Content ArticleIn this study, 156 participants were recruited and randomised to placebo (n=83) or ketamine (n=73), stratified by centre and diagnosis: bipolar, depressive, or other disorders. Two 40-minute intravenous infusions of ketamine (0.5 mg/kg) or placebo (saline) were administered at baseline and 24 hours, in addition to usual treatment. The primary outcome was the rate of patients in full suicidal remission at day 3, according to the scale for suicidal ideation total score ≤3. Analyses were conducted on an intention-to-treat basis. The findings indicate that ketamine is rapid, safe in the short term, and has persistent benefits for acute care in suicidal patients. Comorbid mental disorders appear to be important moderators. An analgesic effect on mental pain might explain the anti-suicidal effects of ketamine. There are also some useful and thought-provoking comments on this research, and a helpful visual aid.
-
Bb9eb4a8277e9d72dd837687465f4857An important message here. Knowing the reason for the use of a medicine (i.e. its 'indication') is vital for patient safety. It's not just pharmacists who need to know the indication for a medicine. In my clinical practice I've seen problems caused by misunderstandings of what a medicine was prescribed for. Including patients who have been prescribed antipsychotic drugs which they did not know the reason for & which could be making their condition worse. Also, I've come across people who were prescribed antidepressants for pain rather than depression (e.g., amitriptyline which is indicated for both things) who believed they were taking an antidepressant and that it 'wasn't working', not knowing that the dose prescribed for pain is lower than that for depression. Many medicines have several different indications, also some medicines are used 'off label' (i.e. for purposes that they are not licensed for). This can be confusing to both patients and clinicians alike, especially when trying to build up a list of previous medicines and what they were prescribed for. I've seen prescribing mistakes made as a result.
-
Bb9eb4a8277e9d72dd837687465f4857An insightful piece, written with objectivity and empathy, highlighting the need for a deeper understanding of why people speak up in healthcare and the consequences for us all when patient safety concerns are dismissed. All healthcare leaders should read this and reflect on how effective current measures are, and what actions are needed.
-
Community PostThe West Suffolk Independent Review published yesterday indicates that safety concerns were ignored and the hunt for an anonymous whistleblower was "flawed" and "ill-judged". https://www.england.nhs.uk/east-of-england/wp-content/uploads/sites/47/2021/12/west-suffolk-review-081221.pdf This Review was commissioned following widely reported events arising from an anonymous letter that was sent in October 2018 to the relative of a patient who had died at the West Suffolk NHS Foundation Trust (the Trust). The 225 page report contains important learning and highlights the need for an open culture in the NHS and an end to a culture of avoidance, denial and victimisation of those who speak out for patient safety. This report highlights the need for cultural change and raises several key points: The importance of real and empowered clinical leadership. The importance of NHS leaders being self-questioning, open to criticism and to listen to staff. The importance of leaders understand the value of dissent and disagreement. Where concerns and criticisms appear or do turn out to be misguided, the need for NHS leaders to avoid jumping to any conclusion that the individual raising them is simply making trouble.
-
Community PostSteve Turner replied to Dominic Stenning's topic in Human factors (improving human performance in care delivery)I am so sorry to hear of your experience Dom. As a mental health nurse who trained in the 1980s I have witnessed a shocking decline in the NHS. The NHS being an institution which, like you, I support and want to see thrive and become world class. The NHS, and indeed all services commissioned by health & social care, has fallen victim to a culture of avoidance, a rise of cronyism (based on self-interest) and exclusion of those who speak out. That includes appalling treatment of patients and relatives who speak out. This has to change. In order to change this problem has to be fully recognised, independently scrutinised, and spoken about openly at the top, not avoided and skirted around, as is currently happening for example through the weak implementation of the Francis Review recommendations and stigmatisation of many who who speak out.
-
Content ArticleIn this video of a plenary session from the Guidelines International Network (GIN) Conference on 26 October 2021, James McCormack, Professor at the Faculty of Pharmaceutical Science, University of British Columbia, discusses issues with clinical practice guidelines and ways to overcome them.
-
Content ArticleThe Global Drug Policy Index provides a score and ranking for each country to show how much their drug policies and their implementation align with the UN principles of human rights, health and development. It offers an important accountability and evaluation mechanism in the field of drug policy.
-
Bb9eb4a8277e9d72dd837687465f4857Excellent poster. Good to see scientific rigour applied to this safety critical topic. In my view, this provides and important and stark contrast to the pseudo-science and waffle produced by the National Guardian Office.
-
-
Content ArticleIt's that time again. 'Speak Up Month' in the NHS. In this blog, I discuss the definition of 'whistelblowing' and why this is important. I believe that although the Francis Report has stimulated some positive changes, the only way to successfully move forward on this is to celebrate and promote genuine whistleblowers. This includes using the word 'whistleblowing', not a euphemism. It also needs us to involve everyone, including patients, in the changes. "Whistleblowing isn’t a problem to be solved or managed, it’s an opportunity to learn and improve. The more we move away for labelling and stereotyping the more we will learn. Regardless of our position, role or perceived status, we all need to address this much more openly and explicitly, in a spirit of truth and reconciliation." What is whistleblowing? "In the UK, NHS bodies have been guilty of muddying the waters. Sometimes implying that whistleblowers are people who fail to use the proper channels, or are troublemakers, especially when they go outside their organisation with their concerns. In fact, the Public Interest Disclosure Act makes no distinction between ‘internal’ and ‘external’ whistle-blowers..."
-
Community PostThat would be good. I wonder how common experiences of bouncing, delayed or lost referrals are are. There is so much learning to be had. Including simple changes that can be made right now to improve communication and the safety of referral processes. Thank you.
-
Community PostI have a family member who had a similar experience to the one you describe Helen. This involved an urgent tertiary referral that would have been bounced back to the patient had they not kept their own notes. As he had the notes my relative was able to show copies of all the letters, scans, EEGs and reports that indicated the referral was potentially life saving. In his case I believe his GP would have intervened, however the GP did not have all the notes and was missing a key echo-cardiogram, that showed definitively an urgent intervention was needed. My recommendation to all patients is to keep a copy of your notes in real-time. Insist that everything is copied to you. Most clinicians are more than happy to do this. (They all should be!) Then, if your referral goes in to a faceless 'referral management system', it is less likely to be lost or the priority to be missed. My worry is that this is fine for articulate, English speaking, reasonably IT literate, middle class white people like me. What about those who slip through the net? Who helps them? Who advocates for them? We may never hear of this.
-
Content ArticleThe government commissioned Dr Keith Ridge, Chief Pharmaceutical Officer for England, to lead a review into the use of medication and overprescribing.
-
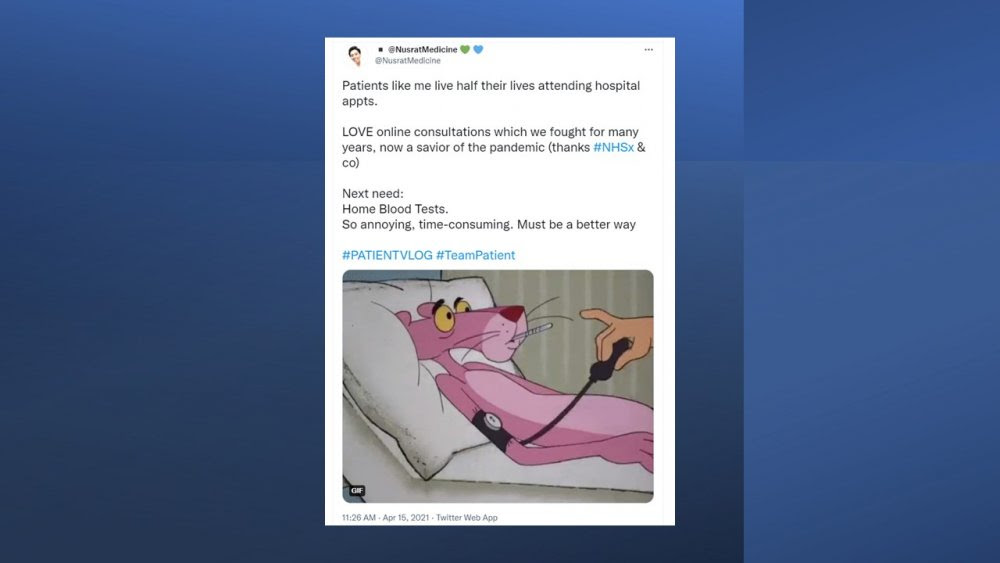
Bb9eb4a8277e9d72dd837687465f4857A really helpful article picking up on the key points. In my recent experience of providing remote 'patient led medicines reviews' I'd also add that this isn't just about Doctors, remote consultations (where appropriate) open up many new possibilities for new ways of working by all clinicians. I use them for my developing work as a Care Navigatior . I'm pleased to see the “remote by default” message challenged. This was such a bad thing to say and harks back to the old way of thinking that technology is the answer to healthcare problems, when it's just a tool. A Secretary of State for Health and Social Care should know this. Finally it's worth remembering that digital consultations aren't something the NHS has just discovered and is now 'educating' patients on. Many patients have been asking for this for years. This tweet sums it up nicely: Source : https://twitter.com/NusratMedicine/status/1382641585184210944?s=20
-
Content Article
 This competency framework has been developed and updated to support prescribers in expanding their knowledge, skills, motives and personal traits, to continually improve their performance, and work safely and effectively.
-
Bb9eb4a8277e9d72dd837687465f4857A good article. I agree in principle too with 'raising concerns in the right way', however my experience, and that of many others, is that this isn't always possible. We need more CEOs like David Carter, and we need to expose CEOs who victimise those who raise genuine concerns.
-
Content ArticleIn this article in the Pharmaceutical Journal, Carolyn Wickware asks if liquid morphine should be reclassified. She cites research that Oramorph or oral morphine sulphate solution was directly linked to the cause of death in 13 reports since 2013.
-
Bb9eb4a8277e9d72dd837687465f4857Robert Darren Powell, a much loved member of a close family, was just 10-years old when he died on the 17th April 1990. Every parent’s worst nightmare, the tragic loss of a child, became Will and Diane Powell’s lived reality. Their acutely distressing grief, was exacerbated because they quickly learned that Robbie’s death was preventable. Little did they know back in 1990 that their pursuit for truth, justice and accountability would span across three decades, cost them in-excess of £300,000 in compensation, and unveil medical negligence, cover-ups and bureaucratic failure. ' The shocking story of a cover up in the UK healthcare system. It is THE landmark case on #DutyofCandour . As a clinician I am appalled, and support Will Powell in his continuing quest for justice. Because of the cover up vital learning on #patientsafety , particularly around the care of children and communication with parents, has been missed. https://www.open.ac.uk/researchcentres/herc/blog/robbie-powell-time-truth-justice-and-accountability https://www.pslhub.org/learn/investigations-risk-management-and-legal-issues/english-and-welsh-ombudsman-set-out-the-case-for-a-proper-public-inquiry-into-the-tragic-death-of-robbie-powell-r3560/?tab=comments#comment-334 https://twitter.com/MedicineGovSte/status/1424353716040343557?s=20 https://www.youtube.com/playlist?list=PLPtuApYs79-6ie3tnwTpONsxjzc5ooG4d
-
Bb9eb4a8277e9d72dd837687465f4857This 'fortress mentality' & similar attitudes have been around for a long time. I'm a strong supporter of the NHS and its core principles. At the same time, having worked in the private sector, for a US company & in Australia, I can also see why people raise concerns about the downsides of so-called 'socialised medicine'. It's the often mentality that's the problem in my opinion, and this can be reinforced by the leadership and the surrounding bureaucracy. Here's an example from some years ago, which I think is still relevant: I was doing a review of waiting list administration in an NHS hospital that had a military wing. The civilian consultants had very long waiting lists, the militarily consultants did not. I assumed that was because they had fewer referrals to manage. When I looked into it this, I found it was not the case. So I asked one of the military consultants what they did to successfully manage their waiting list. He said 'it's simple, I look through the list myself every week and if I have a backlog or urgent referrals to be seen I add a clinic and do what's needed'.
-
Bb9eb4a8277e9d72dd837687465f4857Great to see this promoted. I will be using this poster in my Clinical Education work & my clinical practice . Thank you David Havard, this is really helpful.


