


Steve Turner
Members
-
Joined
-
Last visited
Everything posted by Steve Turner
-
Content Article
 The UK health service is often criticised for working in silos. Patient safety campaigners, policy makers and support organisations frequently do the same. This opinion piece sets out a way to supercharge patient safety improvements. Are you setting up a patient safety event or initiative? Have you involved the right people? What are your aims and objectives? How will you evaluate progress? This article outlines the 'four pillars of patient safety' approach for patient safety initiatives, workshops and events. It draws together areas that are critical for patient safety. It is based on my experience of working across boundaries on large-scale events and challenges the current practice of working in silos. The reflection includes how to validate the model and use it in practice. It is a call to action that challenges the patient safety world to be more inclusive, engage openly across professions and disciplines, and to include patients.
-
Content Article CommentPetition for a Robbie's Law: https://www.change.org/p/implement-legislation-for-individual-legal-duty-of-candour-for-all-public-officials
-
Content ArticleThis article offers a socio‑legal analysis and reflection on the Robbie Powell case, drawing on official reports, legal judgments, investigations and subsequent policy reforms. It highlights an unequal fight for the truth. Reinforcing why Robbie’s Law must stand beside Hillsborough Law. When justice depends on a family’s social capital, not the facts, cases like Robbie Powell’s are sidelined—yet his fight for an individual Duty of Candour strengthens every truth‑and‑justice campaign, not least Hillsborough Law.
-
Content Article CommentWhilst I support the NHS staff survey I believe it is important to point out that it isn't fully anonymous and that this may influence whether or not people respond. It's labelled as 'anonymous', but results are reported at team/group level. As I understand it all findings are reported back to the Trust as an overall picture and by teams of 11 or more. So while individual responses aren't traceable back to a named person, the results are broken down and reported at team/directorate level. In a small team, even aggregated results could potentially allow managers to infer who said what. This does risk putting people off responding.
-
Content Article CommentSteve Turner commented on Steve Turner's article in Investigations, risk management and legal issuesI hope as many people as possible read, reflect, comment and join the debate. The arguments against an individual legal duty of candour in healthcare are mostly invalid in my view. The subject is often deliberately avoided by people in power, possibly because people know the arguments against it are so weak. I used to cover this in my pre and post graduate teaching on accountability & was always shocked at how little professionals knew about the subject and its history.
- 4 comments
-
1
-
- Accountability
- Behaviour
- Clinical process
- Code of conduct
-
Tagged with:
-
Content Article
 More than three decades after the preventable death of 10-year-old Robbie Powell, the UK still does not have a legal mechanism to hold individual clinicians accountable for dishonesty. This evidence-based opinion piece from Steve Turner argues that an ethical code of conduct is not sufficient to ensure accountability and that an individual legal duty of candour is essential for patient safety. It makes the link between Hillsborough Law and Robbie's Law.
- 4 comments
-
1
-
- Accountability
- Behaviour
- Clinical process
- Code of conduct
-
Tagged with:
-
Content Article"Our #health system in the UK is in a mess. It has failed to modernise (by this I mean to become fully accountable to #patients and the public, and truly patient-led). Instead, the system has become more and more hierarchical, bureaucratic and crony ridden, mostly as a result of constant meddling and pointless reorganisations instigated by politicians. All political parties in government for the past 30 years have had a hand in this decline." This is my view? What is yours? A new Inquiry gives us all an opportunity to have our say. I am proud to have worked in and for the NHS for most of my working life; proud to have been trained in the #NHS and proud of the work being carried out by clinical teams today. Great work which has benefited patients, often not because of the leadership but despite of the leadership. I'm retired so I can say what I like. If I were working and said anything even vaguely like criticism, however constructive it was, I would be out of a job and my career would be blighted for life. I'm speaking from experience here, unfortunately. I urge everyone to respond to the consultation (link below). In your response think forensically and write it as a statement of truth. Acknowledge the successes and areas that have delivered safe and effective services. If you are being critical give examples and say if it is an opinion or back up what you say with evidence. If we work together across boundaries we can
-
Content Article CommentTime to act. Time to actually learn lessons. Time to change the law to protect patients. Time to join the dots and prevent further tragedies. There is an opportunity to link the planned inquiry, which I agree must be a statutory inquiry, to the current government review of the whistleblowing framework: framework: https://www.gov.uk/government/publications/review-of-the-whistleblowing-framework/review-of-the-whistleblowing-framework-terms-of-reference
-
Content ArticleThis YouTube playlist containing 12 short vlogs (each lasting 10 minutes or less) is a cut-down version of Continuing Professional Development work commissioned by the NHS in England. These are part of our patient led clinical education work and involved working with patients, carers, and relatives as equals to produce the videos. These vlogs are based on the (UK) Royal Pharmaceutical Society Competency Framework for all Prescribers, and related guidelines from professional bodies in the UK. They are designed for clinicians (across all disciplines and specialities), patients, carers, parents, relatives and the public. The short videos focus on providing refresher information, updates on hot topics and materials that can be used for reflection both individually and within clinical teams. They cover: Shared decision making Information mastery Interpretation of numerical data Root causes on medicines and prescribing errors Taking a history Basic pharmacology Risk areas and red flags Ethics, the law and prescribing Deprescribing Remote prescribing Prescribing for frailty and multimorbidity Prescription writing and safe prescribing The original materials were accompanied by live sessions, questions for reflection (some of which are included here), separate refresher questions, detailed prescribing scenarios, and competency assessments.
-
Content Article CommentThis important report highlights the #patientsafety minefield that exists in the UK. It is characterised by a fragmented system with both overlaps and gaps, plus very few opportunities for inter-disciplinary / inter-organisational learning. Featuring: - A Patient Safety Commissioner whose remit is limited to medicines and medical devices - A plethora of organisations that 'don't investigate individual concerns' (including Healthwatch and the Patient Safety Commissioner) - A lack of genuine patient involvement - A lack of ownership and leadership at the top #share4safety #health #healthcare #nhs #socialcare
-
Content Article CommentI'm a nurse. I believe in the principle of 'do no harm' So I don't support this initiative in its current form and advise people to take care if they are thinking of talking to the local guardian. They may be able to help, or they may make the situation worse. It depends on their employer. The introduction of the National Guardian Office and Freedom to Speak Up Guardians in each NHS trust is problematic. This initiative has an inbuilt conflict of interest, as the Guardians are employed by the trusts themselves. Whistleblowers who have been failed by local Guardians have shared their experiences that included the disclosure of their identity to hospital management and boards, which resulted in retaliation. I also know of Local Guardians who were not supported and themselves the target of retaliation after supporting whistleblowers. In addition, the National Guardian Office appears to studiously avoid the word ‘#whistleblowing’ in its material and outputs wherever possible. This adds to the stigma around healthcare whistleblowers and is inexcusable. This potential for harm because the Guardians are employed by the trusts is a #patientsafety issue and something that the National Guardian Office should be addressing. Instead, the NG Office seems impossible to engage, with unless you agree 100% with their views and become one of their 'cheerleaders'. Patients deserve better.
-
Content Article CommentA useful document from the DHSC. It contains vital information for NHS leaders, board members and educators. One anomaly stands out, however. The report lists one of the 'substantial measures' introduced in the last decade as 'legal protection for whistleblowers'. I'm at a loss to know what these improved legal measures are?
-
Content Article CommentThanks for sharing this important summary of the current harmful system for healthcare whistleblowers. I agree 100%, that the current system of governance fails whistleblowers. In fact, it fails everyone. It appears to be set up this way be design, rather than inadvertently. It's indefensible to have a system whereby the patients and relatives must struggle to have someone independently investigate their concerns, and staff who speak out are victimised and silenced. Even Healthwatch, as I understand it, doesn't investigate individual concerns. You couldn't make this up! Recently I replied to a HSIB survey asking if they investigated 'systematic problems' and the reply was that they don't. So that limits their helpfulness even more. This blog on HSIB and why it has been stripped of maternity investigations, is also interesting & relevant: https://minhalexander.com/2023/04/26/finally-revealed-the-suppressed-susan-newton-report-on-whistleblowing-governance-at-hsib-nhs-england/
-
Content Article CommentThanks for the comments. These are important points. I agree that U.S. bounty model of “whistleblowing” rewards would be inappropriate for the UK, and the way in which the Office of The Whistleblower provides independent oversight of whistleblowing will be critical. For me, the strengths of this approach are that it crosses all sectors and will include perspectives from other countries. I hope and expect that the core issues relating to whistleblower victimisation in health & social care will surface as a result, so they be dealt with effectively and patients protected. For me, the core issues include those related to leadership style & behaviour, nepotism & cronyism, governance, patient and public involvement, accountability, long-term planning, information and record sharing. If you are interested in patient safety, please read the Protection for #Whistleblowing Bill and assess for yourself the impact this will have, don't rely on someone else's summary of the Bill. 'The Public Interest Disclosure Act [PIDA] fails to address the public interest. PIDA turns patient safety concerns into employment issues. It kicks in after the harm has been done, turning a public interest matter into a costly private dispute. Taking the focus off the core issues. Further harming everyone involved in speaking up. The Office of the Whistleblower will strengthen existing initiatives and bring them together, emphasising prevention and early intervention by the most appropriate route. Right now, there is an elephant in the room. Where staff can't, or don't blow the whistle or are ignored or silenced, the onus to expose wrongdoing falls on patients and their relatives who then have no protection under #PIDA. Their concerns are often treated as individual cases and core learning, which would make services safer across the board, are delayed or even lost.' More information here: Read the Bill here: https://www.appgwhistleblowing.co.uk/ Here's a summary of the benefits of the Protection for Whistleblowing Bill [HL] comparing it to current law.

-
Content Article
 In this blog, Steve Turner reflects on why genuine patient safety whistleblowers are so frequently ignored, side-lined or victimised. Why staff don't speak out, why measures to change this have not worked and, in some cases, have exacerbated the problems. Steve concludes with optimism that new legislation going through Parliament offers a way forward from which everyone will benefit.
-
-
Content ArticleThis short blog highlights the situations where patients, carers, parents and relatives are failed by healthcare systems and by the leadership. They are left to stand alone against powerful institutions, because when staff speak up and 'blow the whistle' it often results in retaliation. Investigating and resolving the patient safety issue then becomes buried under an employment issue.
-
Content ArticleIn December 2022, the All Party Parliamentary (APPG) for Whistleblowing heard evidence on the state of the NHS following the recent report on the avoidable deaths and life changing injuries caused to mothers and babies at the East Kent Trust. The culture at this hospital was described as one where “everyone knew the problems” and where whistleblowers were “thrown to the lions”. A culture attributed to 45 of the 65 baby deaths reviewed. This blog first appeared on the Whistleblowers UK website in December 2022.
-
Content Article CommentTime to examine the root causes of why these reports continue to show that lessons have not been learned. Three areas of concern stand out for me: 1. There is no independent official body that looks at systemic failings in #healthcare in the UK. (I understand that the remit of the Health & Safety Investigation Branch [HSIB] specifically excludes this). 2. There is no clear pathway that triggers major reviews of healthcare failings. (More often than not these shocking reports are prompted by #patients and their families). 3. When staff feel unable to blow the whistle, or are ignored and victimised for doing this, relatives take this on, at great personal cost. (Examples of where staff have not raised concerns or have had their concerns dismissed, include the death of Robbie Powell, Elizabeth Dixon, Oliver McGowan, Claire Roberts and ‘Gosport.) For too long inexcusable failings have been covered up. It's frequently said that it wasn't because nobody knew about it. It was something that everyone knew about. In the words of the late Professor Aidan Halligan, we need to 'Run toward problems, especially on a bad day'.
-
Community PostIs it time to change the way England's healthcare system is funded? Is the English system in need of radical structural change at the top? I've been prompted to think about this by the article about the German public health system on the BBC website: https://www.bbc.co.uk/news/health-62986347.amp There are no quick fixes, however we all need to look at this closely. I believe that really 'modernising' / 'transforming' our health & #socialcare systems could 'save the #NHS'. Both for #patients through improved safety, efficiency & accountability, and by making the #NHS an attractive place to work again, providing the NHS Constitution for England is at the heart of changes and is kept up to date. In my experience, having worked in healthcare for the private sector and the NHS, and lived and worked in other countries, we need to open our eyes. At present it could be argued that we have the worst of both worlds in England. A partially privatised health system and a fully privatised social care system. All strung together by poor commissioning and artificial and toxic barriers, such as the need for continuing care assessments. In my view a change, for example to a German-style system, could improve patient safety through empowering the great managers and leaders we have in the NHS. These key people are held back by the current hierarchical crony-ridden system, and we are at risk of losing them. In England we have a system which all too often punishes those who speak out for patients and hides failings behind a web of denial, obfuscation and secrecy, and in doing this fails to learn. Vast swathes of unnecessary bureaucracy and duplication could be eliminated, gaps more easily identified, and greater focus given to deeply involving patients in the delivery of their own care. This is a contentious subject as people have such reverence for the NHS. I respect the values of the NHS and want to keep them; to do this effectively we need much more open discussion on how it is organised and funded. What are people's views?
-
- Accountability
- Behaviour
- Benchmarking
- Change management
-
Tagged with:
- Accountability
- Behaviour
- Benchmarking
- Change management
- Clinical governance
- Collaboration
- Communication problems
- Culture of fear
- Decision making
- Duty of Candour
- Hierarchy
- Just Culture
- Leadership
- Organisation / service factors
- Organisational culture
- Organisational development
- Organisational learning
- Resources / Organisational management
- Safety culture
- Speaking up
- Staff support
- System safety
- Transformation
- Transparency
- User centred design
- Whistleblowing
-
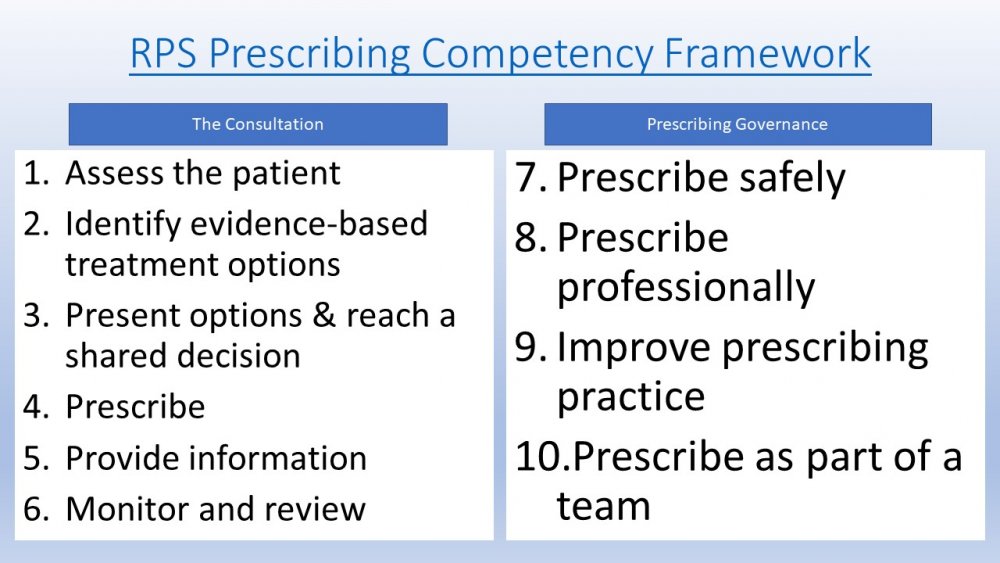
Content Article CommentA significant role for the new Patient Safety Commissioner, in my view, will be through reference to improving prescribing competency, as set out in the RPS Prescribing Competency Framework. A framework which is for ALL prescribers. When speaking the 'truth to power' & reflecting on medicines' safety this framework is key. Link: https://www.rpharms.com/resources/frameworks/prescribers-competency-framework
-
Content Article CommentI believe a review of the corporate governance of #health & #socialcare services in England is needed. This review need not be a long-winded process. There are many studies and reports available, this is the starting point. Plus, the #NHS constitution for England, which rarely gets a mention. Sadly, I don't think this will happen. The overriding ethos is to avoid confronting problems that could make the 'great and the good' look bad & break down the widespread rampant cronyism which is holding back the development of services and driving staff away. #Patients suffer as a result. #leadership #ethics #accountability #whistleblowing #whistleblower #share4safety 'Almost all whistleblowing creates positive change in the organisation which has its wrongdoing reported. Whistleblowers uncover 43% of corruption, compared to only 19% discovered by paid auditors. Whistleblowers lead to the recovery of enough money to give everyone on the planet, health care, many times over.' - WhistleblowersUK
-
Content Article CommentI find it shocking that the proposed reforms, listed below, are not already in place: patient involvement in complaints investigations the establishment of independent investigation bodies more meaningful data analysis strategies to uncover and address systemic causes behind recurring complaints. Perhaps people who are involved with complaints handling, and those who have made complaints can share their experiences? Good or bad experiences - all will contribute to further learning and help deliver real change.



-
Content Article"The inestimable, magnificent, Will Powell speaking on Radio Ombudsman about the long struggle to discover the truth about his son's death and the subsequent failure of accountability mechanisms" - Rob Behrens, Parliamentary and Health Service Ombudsman UK, Vice-President IOI Europe, Visiting Professor UCL. MCFC.
-
Content Article CommentI am so saddened to read yet another report on failings that, if seen and acted on in isolation, will not lead to the systemic changes that are needed. I agree with the conclusion. The approach to patient safety needs to change. This is the 'modernisation' our health and social care services desperately need. No more 'lessons will be learned' statements without follow up, and no more 'sorry-not-sorry' apologies, we need radical patient-led change, transparency, and accountability.


